Why You Are Measured Shorter at the Doctor's Office Than You Think You Are
Quick Answer: Three things explain most of the gap. First, you are genuinely shorter in the afternoon than in the morning - spinal discs compress under bodyweight through the day, typically costing 1 to 2 centimetres. Second, most people are comparing against a number measured in their late teens, sometimes without shoes off or with a poor technique. Third, gradual height loss from the mid-40s onward is normal and slow. What is worth mentioning to a doctor is fast loss - more than about 2cm in a year, or 4cm from your peak adult height - which can be a marker of bone density change.
You have said the same number for twenty years. Then the nurse slides the bar down, writes something on the chart, and it is not that number.
The reflex is to assume the measurement is wrong. Usually it is not wrong - it is just measuring something more precisely than the number in your head ever was.


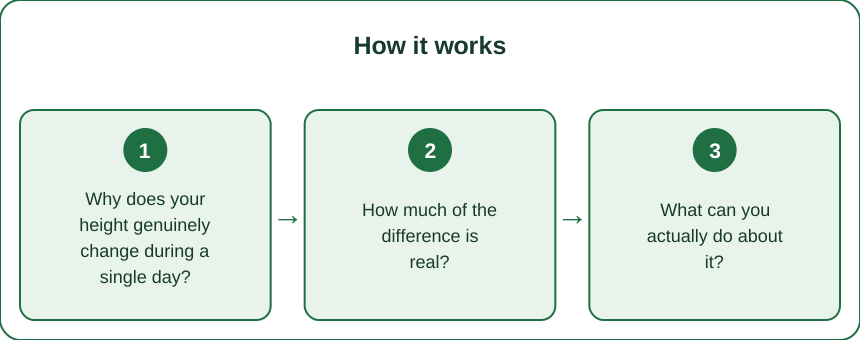
Why does your height genuinely change during a single day?
Your spinal discs are compressible, and they spend all day being compressed.
Between each pair of vertebrae sits an intervertebral disc with a gel-like core that is largely water. Standing, sitting, walking, and lifting all apply axial load to those discs, and through the day fluid is gradually squeezed out of them. Overnight, lying horizontal removes the load and the discs rehydrate.
The measured effect is consistent: most adults lose somewhere between one and two centimetres between waking and evening, with most of it happening in the first few hours after getting up. Spinal researchers have used this for decades as a way to study disc loading, and it is pronounced enough that studies on astronauts - who gain height without gravitational loading - are a well-known example of the same mechanism running in reverse.
So an 8am appointment and a 4pm appointment will genuinely produce different numbers on the same person in the same week.
What else moves the number on the day:
Posture during measurement. A proper measurement has heels together, back against the wall, and the head positioned so the line from the ear canal to the lower eye socket is horizontal. Chin tilted up adds height; slouching removes it. Different people measuring you will get different results by half a centimetre or more.
Shoes and hair. Obvious and still common. Thick socks and a high bun both count.
Recent activity. An hour of running or heavy lifting compresses the discs measurably. So does carrying a heavy bag. If you came from the gym, you will measure slightly shorter than if you came from your sofa.
How much of the difference is real?
Some, and how much depends mostly on your age and your reference number.
The reference number is usually the problem. Most people are comparing against a height recorded in adolescence or early twenties, often self-reported, sometimes measured with shoes on. Self-reported height is well documented as running slightly above measured height, and the gap tends to grow with age as people keep quoting an old number.
In other words, the discrepancy is often not that you shrank. It is that you were never quite that tall to begin with, or that nobody measured carefully.
Genuine age-related height loss is real and gradual. Adults typically begin losing height slowly from around the mid-40s, and the rate increases somewhat after 70. The usual figure quoted is around a centimetre per decade in mid-life, accelerating later, with women generally losing somewhat more than men over a lifetime.
Three mechanisms drive it:
Disc thinning. Discs lose water content permanently with age, not just daily. This accounts for a good share of mid-life loss.
Postural change. Increased thoracic curve from weakened postural muscles and habitual position. Some of this is genuinely reversible with strength work.
Vertebral bone changes. Reduced bone density can lead to small compression fractures in the vertebrae, often without any symptoms. This is the one that matters medically.
The threshold worth mentioning to a doctor: losing more than about 2cm in a single year, or more than about 4cm from your peak adult height, is worth raising - it is one of the recognised clinical prompts for considering bone density assessment. Slow, gradual loss in your 50s is expected. Rapid loss is information.
This is general information, not medical advice. If you have concerns about height loss or bone health, talk to your doctor.

What can you actually do about it?
Some of it is preventable, some is postural and genuinely reversible, and the rest is worth measuring properly.
Protect bone density, which is the part that matters most:
- Resistance training and impact. Bone responds to load. Weight-bearing exercise and resistance training are the best-evidenced non-pharmaceutical interventions for maintaining bone density, and they work at any age.
- Adequate calcium and vitamin D. Vitamin D status is worth actually testing rather than assuming, particularly at northern latitudes going into autumn.
- Protein intake. Frequently under-consumed in older women and directly relevant to both bone and the muscle that supports posture.
- Smoking and heavy alcohol both accelerate bone loss substantially.
Address the postural component, which is often the visible one:
- Thoracic extension work. The rounded upper back that develops from years of desk work costs real measurable height and responds to targeted mobility and strengthening.
- Strengthen the posterior chain. Rows, face pulls, and back extensions counteract the forward-rounded pattern.
- Core and hip work supports neutral spinal alignment.
People who take up structured strength training in mid-life frequently gain back a centimetre of apparent height, purely from posture. That is not a trick - it is the difference between a slumped and an upright spine, and it is a genuine measurement.
And measure it consistently:
If you want to track this meaningfully, measure at the same time of day - ideally mid-morning, at least two hours after waking - without shoes, against a wall, with your head level. Once a year is plenty. A number taken at 8am and compared against one taken at 6pm will tell you nothing except what you already know about discs.
Myth vs Fact: Height and Aging
Myth: Losing height means you have osteoporosis. Fact: Gradual loss is a normal part of aging and mostly reflects disc changes and posture. Rapid loss - roughly over 2cm in a year - is the pattern that warrants investigation, not slow change over decades.
Myth: Hanging from a bar makes you taller. Fact: Spinal decompression through hanging or inversion produces a genuine but temporary effect, on the same order as the daily variation. It reverses within hours of standing. It does not add permanent height, though it may feel good.
Myth: You stop growing at 18 and stay that height until old age. Fact: Most people reach peak height in their late teens to early twenties and hold roughly steady until the mid-40s. It is a plateau, not a permanent fixed value.
Myth: Height loss is inevitable and there is nothing to do about it. Fact: The bone density component responds meaningfully to resistance training, nutrition, and not smoking. The postural component is often partly reversible. Only the disc component is genuinely unavoidable.
Myth: The doctor’s measurement is unreliable so it does not count. Fact: A wall-mounted stadiometer with shoes off is considerably more accurate than however your height was recorded at school. If the numbers disagree, the clinical one is usually the honest one.
FAQ: Height Measurement Questions, Answered
What time of day should I measure to get my real height?
Mid-morning, roughly two to three hours after getting up - by then the initial rapid compression has happened and the slow afternoon decline has not. Most importantly, use the same time every year so the comparison means something.
I lost 3cm since my twenties and I am 55. Should I worry?
Probably not on its own, but it is worth mentioning at your next appointment, particularly if you have other bone density risk factors such as family history, early menopause, or long-term steroid use. Your doctor can tell you whether a scan is appropriate.
Can bad posture alone account for a couple of centimetres?
Yes, comfortably. An increased thoracic curve from years of desk work can account for a centimetre or two, and a good deal of it is recoverable with consistent thoracic mobility and posterior chain strengthening.
Does being taller in the morning mean I should train then?
Not for height reasons, though it is a real phenomenon. Worth noting that discs are at their most hydrated and least compressible first thing, which is one reason some strength coaches suggest avoiding heavy loaded spinal work in the first hour after waking. The evidence there is mixed rather than settled.
TL;DR:
- You are genuinely 1 to 2cm shorter in the evening - spinal discs compress under bodyweight through the day.
- Most of the gap is the reference number, which was often self-reported or measured badly in your teens.
- Real age-related loss starts around the mid-40s and runs roughly a centimetre per decade at first.
- Rapid loss - over 2cm in a year or 4cm from peak - is worth raising with a doctor as a bone density prompt.
- Resistance training, vitamin D, calcium, and protein protect the part that actually matters.
- The postural centimetre is often recoverable with thoracic mobility and posterior chain work.
If the chart said something you did not expect, the useful response is not to argue with the stadiometer. It is to note the number, measure again in a year at the same time of day, and pay attention to the rate rather than the value.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
