The Questions Worth Asking at Your Annual Checkup
Quick Answer: The most useful questions at a checkup are about trend and context rather than the current number - how a result compares to your own previous results, what would change the recommendation, and what specifically to do differently before the next appointment. A single value inside a reference range tells you much less than its direction over three years.
You get ten or fifteen minutes, a set of results, and the word ‘normal’. Then you leave, and a fortnight later you cannot remember what any of it meant.


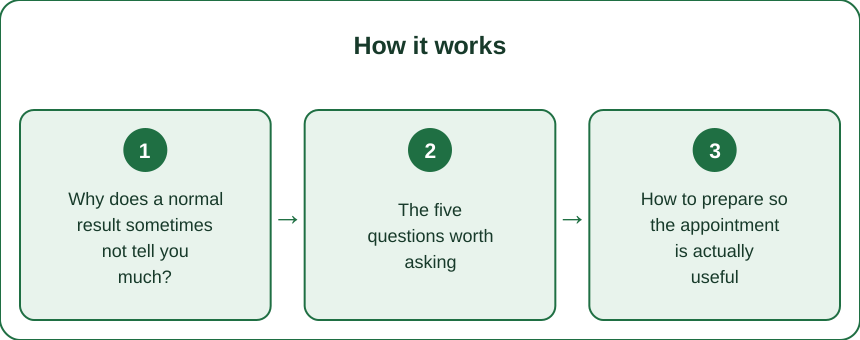
Why does a normal result sometimes not tell you much?
Because reference ranges describe a population, and you are one person moving through it over time.
How reference ranges are built. A range typically represents the central portion of results in a reference population - commonly the middle 95 percent. By construction, about 1 in 20 healthy people falls outside a given range, which is why a single flagged value is usually not alarming on its own.
The corollary that matters more: a value can move substantially within the range and still read as ‘normal’ every time. A result that has gone from the bottom of the range to the top over four years is a trend, and the trend is often more informative than the position.
What this means for how to read your own results:
- Ask for the numbers, not just the interpretation. ‘Normal’ is not a data point you can compare next year.
- Keep them somewhere you control. Practices change, records move, and a personal record spanning several years is genuinely valuable.
- Look at direction across visits, which is the thing nobody does automatically
Where ranges vary and it matters:
- Different labs use different ranges for the same test, so comparing across providers needs care
- Some ranges vary by age, sex and ethnicity, and some do not adjust when arguably they should
- Being at the edge of a range is not the same as being outside it, and neither is automatically a problem
This is general information, not medical advice. Interpreting your own results without clinical context is exactly the failure mode this article is trying to avoid - the goal is better questions, not self-diagnosis.
The five questions worth asking
Question 1: How does this compare to my previous results?
The highest-value question in the appointment. It converts a snapshot into a trajectory, and it prompts the clinician to look at the history rather than the current line.
Question 2: What would have to change for your recommendation to change?
This is the question that reveals where you actually sit. ‘You would need to be above X, or have two consecutive readings above Y’ tells you far more than ‘it’s fine’. It also gives you a concrete threshold to monitor.
Question 3: Is there anything here worth rechecking sooner than a year?
Annual is a default, not a clinical judgement. Some results warrant a three or six month recheck, and that decision often does not get made unless someone asks.
Question 4: Of everything we have discussed, what is the one thing you would change first?
People leave with four or five suggestions and act on none. Asking for a priority order produces one actionable item, which is roughly the number most people successfully implement.
Question 5: What should prompt me to come back before the next appointment?
This is the safety question and the one most often skipped. A clear list of specific symptoms is far more useful than a general instruction to come back if worried.
A sixth, if there is time: are there screenings appropriate for my age or history that we have not done? Screening schedules change, and eligibility shifts with age in ways that are easy to miss.

How to prepare so the appointment is actually useful
Preparation is what determines whether fifteen minutes is enough.
Before the appointment:
- Write down three things maximum. More than three and the important one gets crowded out.
- Lead with the most important item. Appointments run out of time at the end, not the beginning, and the thing mentioned as you stand up gets the least attention.
- Bring a list of medications and supplements, including anything over the counter. Interactions with supplements are a genuine and commonly missed issue.
- Note the timeline of any symptom - when it started, what makes it better or worse, whether it is changing. Timeline is the information clinicians most often have to extract.
During:
- Write down the numbers, not just the conclusions
- Ask for the spelling of anything unfamiliar
- Repeat back the plan in your own words, which catches misunderstandings while you can still resolve them
- Ask what happens next and who is responsible for it - a referral that nobody owns does not happen
After:
- Record the results the same day, in whatever system you will still have in three years
- Put any recheck in the calendar immediately, with a reminder ahead of it
- Note the one priority action, and put a review date on it
On tracking between visits: a small amount of home data - blood pressure readings, weight trend, symptom notes - turns the next appointment from a snapshot into a dataset. Home blood pressure readings in particular are often more representative than a single clinic reading, given how common white coat effects are.
Speak to your healthcare provider about what is appropriate for you. This is general information and does not replace individual medical advice.
Myth vs Fact: Annual Checkups
Myth: Everything in range means everything is fine. Fact: ranges are population-based, and a value that has moved substantially within its range still represents a change. Trend across years carries information that a single in-range value does not.
Myth: One abnormal result means something is wrong. Fact: roughly 1 in 20 healthy people falls outside any given reference range by design. Isolated mildly abnormal results are common and usually warrant a recheck rather than alarm.
Myth: More tests are better. Fact: broad untargeted testing produces false positives that lead to further investigation, cost, and anxiety without improving outcomes. This is why screening guidelines are specific about who should be tested for what.
Myth: You should not ask questions because the doctor knows best. Fact: clinical expertise and your context are different inputs, and the plan works better with both. Questions about thresholds and priorities are standard and useful, not a challenge to anyone’s judgement.
Myth: If they do not call, everything was fine. Fact: results occasionally go astray, and ‘no news is good news’ assumes a system that never fails. Following up on results you have not heard about is reasonable practice, not fussing.
FAQ: Getting More From a Checkup, Answered
What is the single best question to ask?
How this compares to your previous results. It converts a snapshot into a trend, which is where most of the useful information actually lives.
Should I ask for copies of my results?
Yes. Keeping your own record across years lets you and any future clinician see direction rather than a single point, particularly if you change practices.
How many concerns should I raise in one appointment?
Three at most, with the most important one first. Items raised at the end of an appointment reliably get the least time.
Is an annual checkup necessary for everyone?
Recommendations vary by age, risk factors and country, and there is genuine debate about routine annual testing for healthy adults. Ask your provider what schedule suits your situation.
What should I do if a result is slightly outside the range?
Ask what would change the recommendation and whether a recheck is warranted. Mildly abnormal isolated results are common and usually followed up rather than acted on immediately. This is general information, not medical advice.
TL;DR:
- Reference ranges describe populations; your own trend across years carries more information
- Ask how results compare to last time, and what would change the recommendation
- Ask for one priority action rather than leaving with five suggestions and doing none
- Write down the numbers, not the conclusions, and keep your own record
- Ask what specifically should bring you back sooner - the safety question people skip
Fifteen minutes is enough if you arrive with three items and leave with one action and a number. It is rarely enough if you arrive with nothing and leave with the word ‘normal’.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
